Translate this page into:
Idiopathic bilateral uveal effusion syndrome (UES) in a middle-aged woman
*For correspondence: docrishi@yahoo.co.in
This is an open access article distributed under the terms of the Creative Commons Attribution NonCommercial ShareAlike 3.0 License, which allows others to remix, tweak, and build upon the work non commercially, as long as the author is credited and the new creations are licensed under the identical terms.
This article was originally published by Medknow Publications & Media Pvt Ltd and was migrated to Scientific Scholar after the change of Publisher.
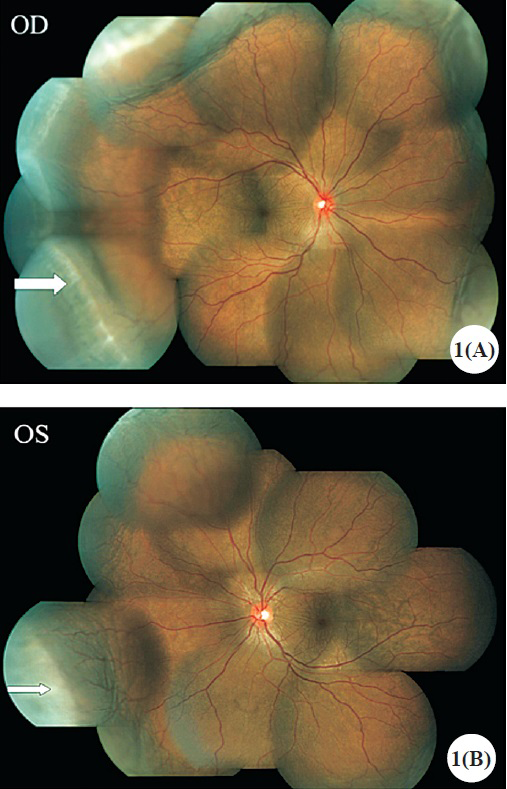
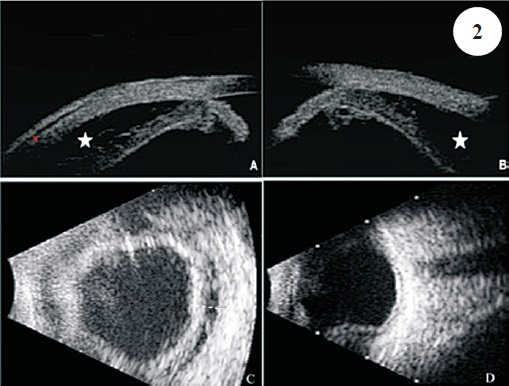
A 44 years old female presented to Vitreo-Retina department of Sankara Nethralaya, Chennai, India, in September 2013 with painful diminution of vision in her both eyes since preceding 10 days. Her systemic and past ophthalmic history was unremarkable. On examination, best corrected visual acuity (BCVA) was 20/30 in both eyes. Intraocular pressure (IOP) was 24 mmHg in both the eyes. Anterior segment biomicroscopy revealed shallow anterior chamber with Shaffer's grade 2 occludable angles. She underwent YAG laser-peripheral iridotomy (LPI) in both eyes. Her fundus examination revealed bilateral exudative retinal detachment with 360° choroidal detachment (Fig. 1A, B). Conventional ultrasonography, ultrasound bimicroscopy (UBM), and fundus fluoroscein angiography ruled out differentials (nanophthalmos, malignancy and inflammatory causes) and confirmed the presence of uveal effusion (Fig. 2).
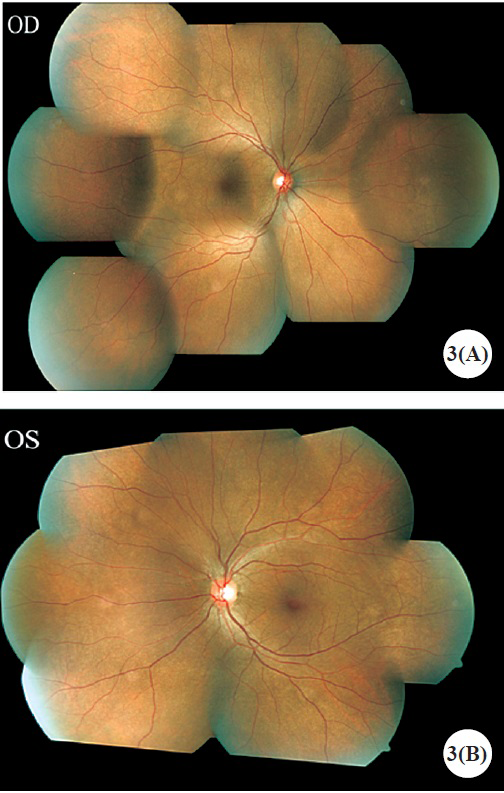
A diagnosis of idiopathic uveal effusion syndrome was made and treatment started with oral prednisolone acetate (1 mg/kg) in weekly tapering doses. At one month follow up her vision improved to 20/20 in both eyes. She responded remarkably well to treatment (Fig. 3A, B). She was maintaining 20/20 vision in both eyes till her last two year follow up visit.